
Health & Science
Robotic heart surgery in Brazil
What the evidence shows about safety and access
Leila Moretti
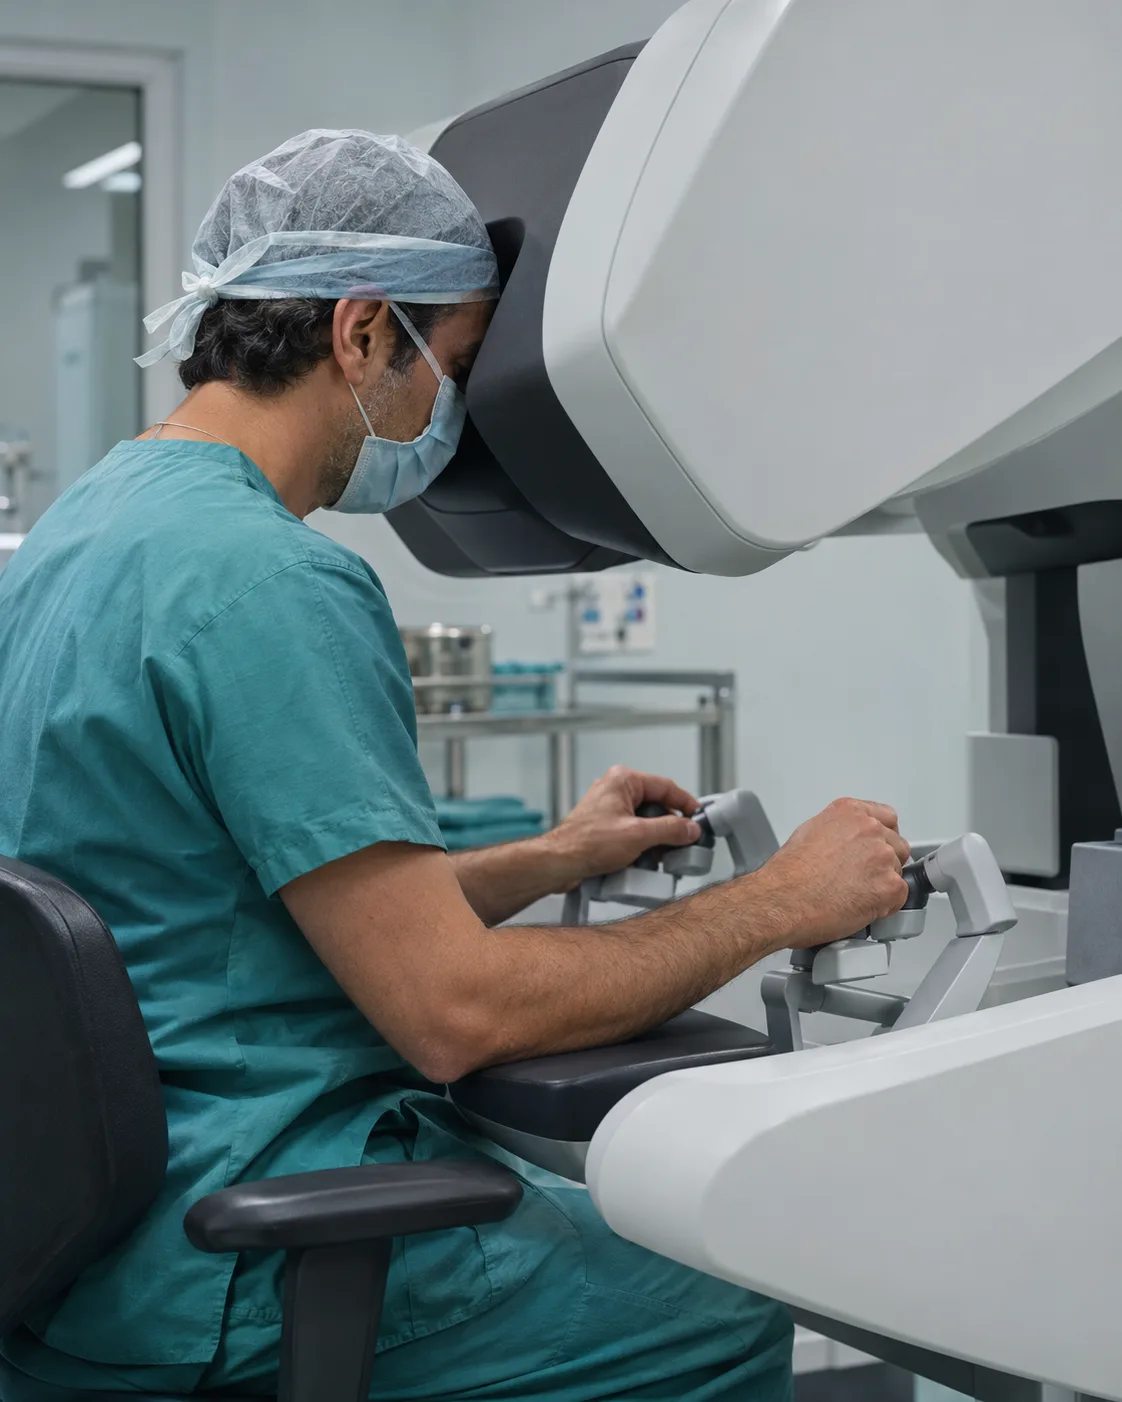
The technique is now an established alternative to sternotomy at leading referral centers in Brazil. The first systematic report of the Brazilian experience, involving 21 patients, helped pave the way, and more than a decade later, the debate over the method no longer centers on safety but on access.
Operating on the heart without cutting through the patient’s breastbone is no longer a possibility limited to a handful of centers abroad. In Brazil, robot-assisted heart surgery is now an established alternative for procedures such as mitral valve repair and replacement, atrial fibrillation correction, removal of intracardiac tumors and coronary artery bypass grafting, always evaluated case by case according to the patient’s surgical risk and anatomical profile.
This path has a clear milestone in the country: the first systematic report of the technique in Brazil, published in the scientific journal Einstein by a team from Einstein Hospital Israelita in São Paulo, led by cardiovascular surgeon Dr. Robinson Poffo.
The study, now a frequently cited reference in later work on the subject, documented a series of 21 patients operated on over three years and sought to answer a straightforward question: was it feasible, and safe, to perform heart surgery in Brazil using the robotic system instead of traditional sternotomy?
What the study showed
All 21 patients gave informed consent and chose the robotic approach after being informed of the surgical options. The study was approved by the hospital’s ethics committee, and data were collected prospectively and recorded in a database created specifically for the project, named the Einstein Registry of Robot-Assisted Minimally Invasive Cardiovascular Surgery.
The procedures performed included mitral valve repair and replacement, surgical correction of atrial fibrillation, atrial septal defect repair, intracardiac tumor resection, totally endoscopic coronary artery bypass grafting and pericardiectomy, in other words, a broad spectrum of cardiac surgeries rather than a single procedure.
Patients’ mean age was 48.4 years. Mean cardiopulmonary bypass time was 151.7 minutes, and mean aortic cross-clamp time was 109.9 minutes. Most patients — 76.2% — were extubated while still in the operating room, right after the procedure, with a mean ICU stay of 1.67 days.
There were no conversions to sternotomy, no in-hospital deaths and no deaths during medium-term follow-up, which lasted a mean of 684 days, ranging from 28 to 1,096 days. The authors concluded that robot-assisted heart surgery proved feasible, safe and effective, and that it can be applied to correct a range of intracardiac and extracardiac diseases.
The limits of a pioneering study
It is worth putting the type of evidence this paper represents into context. It is a single-center case series with no comparison group: there is no arm of patients who underwent conventional sternotomy during the same period to serve as a reference.
The patients themselves chose the robotic approach after being informed about the alternatives, which introduces selection bias, since patients with a more favorable clinical and anatomical profile tend to opt for the newer technique.
With 21 patients, it is also a small sample, insufficient to detect differences in rare complications or to support, on its own, the claim that the method is superior to conventional surgery.
This kind of publication — a report of a pioneering group’s early experience — has a well-defined role and value in the medical literature: demonstrating technical feasibility and the absence of early signs of excessive risk, paving the way for larger studies.
It does not, however, have the design needed to prove one technique superior to another, and the authors themselves make no such claim: the paper speaks of feasibility, safety and effectiveness, not superiority.
What came next
The same team continued the registry. In 2017, it published an analysis of 39 consecutive robotic heart surgery cases in Brazil in the Annals of Thoracic Surgery, and a paper on the initial experience and outlook for the technique in the country in Arquivos Brasileiros de Cardiologia.
Subsequent steps included publications on robotic mitral valve surgery in Latin America and on the national landscape of the technique, gradually expanding the Brazilian evidence base beyond the original series of 21 patients.
According to the institutional website of Dr. Poffo’s own practice, Brazil now has more than 200 robotic platforms installed, a figure that, it should be noted, is self-reported by the surgeon’s own institution and does not come from an independent survey.
These systems, however, are mostly used in other specialties, such as urology and gynecology: robotic heart surgery remains concentrated in a few referral centers, primarily along the Rio–São Paulo corridor.
The real obstacle: access, not evidence
A qualitative review published in 2023 in the Brazilian Journal of Cardiovascular Surgery, by Scudeller and colleagues, specifically addressed the economic and structural barriers to robotic heart surgery in Brazil.
The picture that emerges from the literature on the subject in Brazil is consistent: the obstacle is no longer, as it was in 2013, doubt about whether the technique works; it is the cost of acquiring and maintaining the platforms, the concentration of surgical training in a few private centers and the difficulty of obtaining reimbursement from the health system, public and private, for a procedure that remains expensive.
This pattern repeats itself in other Latin American countries. A 2020 paper in the same journal described how Colombia, despite having advanced in minimally invasive heart surgery since the 1990s, performed its first robotic heart surgery cases well after Brazil, precisely because of limited resources and hospital infrastructure.
A survey of Brazilian urologists, for its part, found that although 75.5% of surgeons performed laparoscopy, only 12.8% performed robotic surgery, with lack of equipment and technical experience emerging as the main barriers.
In an editorial published in 2026 in the Journal of Thoracic and Cardiovascular Surgery, Poffo himself argues that a lack of reliable information — among both patients and referring physicians — still keeps a technology available for more than 20 years from reaching more patients in Brazil.
It is a reading that also serves the interests of those who offer the procedure, but it is consistent with the assessment of structural barriers made by other independent research groups.
The takeaway
More than ten years on, the picture that emerges is this: the safety and feasibility signal observed in the first 21 Brazilian patients held up in the larger series that followed, and the technique has become an established option at referral centers in the country.
What has not advanced at the same pace is access — because of cost, the geographic concentration of expertise and reimbursement difficulties — which today weighs more heavily in the discussion about robotic heart surgery in Brazil than any remaining doubt about its clinical safety.
_____________
Main reference
Poffo R, Toschi AP, Pope RB, Celullare AL, Benício A, Fischer CH, Vieira MLC, Teruya A, Hatanaka DM, Rusca GF, Makdisse M. Robotic surgery in Cardiology: a safe and effective procedure. einstein (São Paulo). 2013;11(3):296-302.
Other studies cited in this article
Poffo R, et al. Robotic cardiac surgery in Brazil: analysis of 39 consecutive cases. Ann Thorac Surg. 2017;103(3):872-878.
Poffo RN, et al. Robotic cardiac surgery in Brazil: initial experience and perspectives. Arq Bras Cardiol. 2017;109(1):85-92.
Montanhesi PK, et al. Robotic mitral valve surgery in Latin America. Ann Cardiothorac Surg. 2022;11(5):540-542.
Scudeller PG, et al. Economic and structural barriers to cardiac robotic surgery in Brazil: a qualitative review. Braz J Cardiovasc Surg. 2023;38(1):93-100.
Andrade D, Vinck EE, Parra JF, Balkhy HH, Núñez F. Robotic Cardiac Surgery in Colombia: Overcoming the Challenges of a Middle-income Setting. Braz J Cardiovasc Surg. 2020;35(6):990-993.


